A gas-tight trocar seal is not a minor convenience. It helps maintain pneumoperitoneum, supports a clear laparoscopic view, and limits repeated insufflator compensation. SAGES clinical guidance describes commonly used working pressures around 12–15 mmHg, making reliable sealing important throughout instrument exchanges. Small leaks matter. Yet pressure alone cannot prove that a seal is performing well.
How to ensure a gas-tight seal with laparoscopic trocars? The answer starts with the complete assembly: cannula, valve, reducer, and instrument. A mismatch, worn valve, or small tear can allow carbon dioxide to escape around a shaft. The FDA’s guidance for medical-device performance testing and ISO 14971:2019 both emphasize risk-based evaluation; neither should be treated as a substitute for device-specific instructions or clinical judgment. Manufacturers’ instructions for use remain essential.
In practice, teams should inspect components, confirm compatible instruments, and assess pressure stability during insertion and exchange. A sudden hiss or falling insufflator pressure deserves attention, though neither is a perfect leak test. Not always obvious. This is where the real-world picture gets messy: seals can behave differently with instrument diameter, angulation, and repeated use. The safest standard is a validated device design, careful handling, and monitoring during the procedure—not a promise that any trocar will remain perfectly airtight.
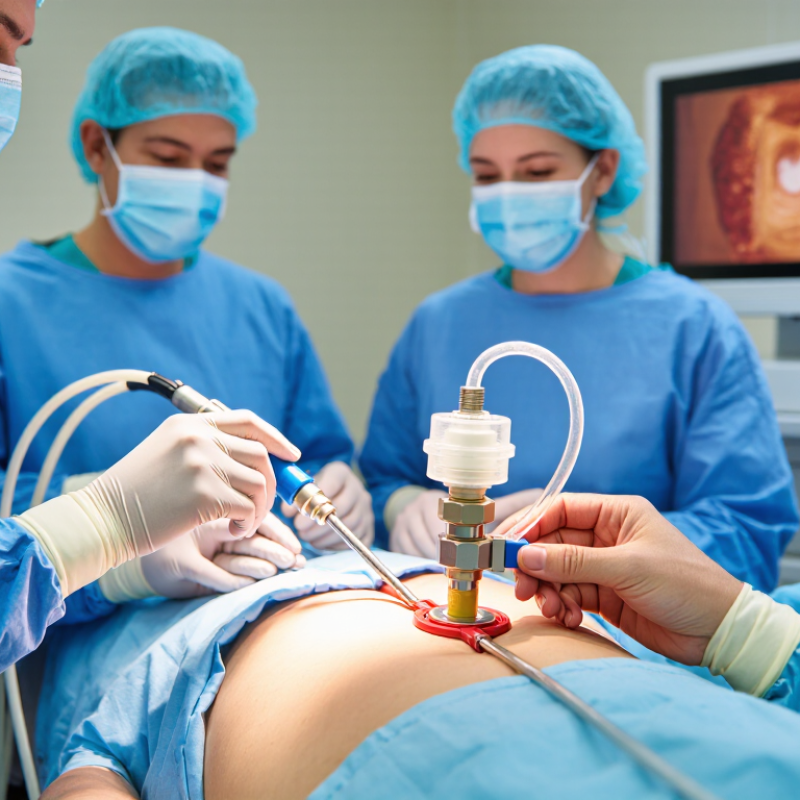
A trocar seal limits gas loss by closing the space around an instrument and sealing the opening when no instrument is present. These functions may be handled by separate valves. The seal helps maintain the working space created by insufflation, but it cannot compensate for every leak elsewhere in the system.
Fit matters. A seal designed for one instrument diameter may not seal well around a much narrower shaft. Slow, straight insertion can reduce stress on the valve; forceful movement may stretch or damage it. During use, teams can check for a falling pressure reading, a hissing sound, or a visibly distorted seal. Small leaks can be easy to miss.
It is tempting to blame the valve alone, but that is too simple. The cannula connection, instrument fit, and insufflator setup can also affect gas retention. Inspect the seal before use, keep it free of debris, and replace damaged components according to the device instructions. Avoid improvised repairs. A quick check between instrument exchanges is useful, though it may not catch every problem. If pressure remains unstable, pause and assess the full setup rather than assuming the seal is sound.
Trocar selection should match the procedure, instrument diameter, and expected number of exchanges. A 5 mm instrument in a 5 mm cannula may seal differently from a larger instrument or an angled shaft. Check the valve design, cannula length, and whether the port will accommodate extraction. SAGES guidance on laparoscopic entry describes insufflation pressures around 12–15 mmHg. That range offers useful context, but it does not prove a trocar will remain gas-tight during every instrument change. Small details matter.
For frequent exchanges, assess how the seal responds when instruments enter, withdraw, and move off-axis. A slit valve and a separate zero-closure valve may behave differently; the intended instruments and procedure should guide the choice. Inspect the seal for damage, confirm compatibility, and follow the device instructions before use. AORN’s Guidelines for Perioperative Practice also emphasize maintaining pneumoperitoneum through appropriate equipment and technique. Bench testing helps, but it cannot reproduce every operating-room movement. I would not treat a low-leak test result as a guarantee: hands, angles, and repeated exchanges can change the picture.
Preparing and inserting the trocar correctly begins before the incision. Confirm that the obturator and cannula are compatible, the valve moves freely, and the seal is clean and undamaged. Check the insufflation tubing and connections, too; a loose fitting can mimic a trocar leak. SAGES guidance describes 12–15 mmHg as a usual working pressure range for laparoscopy. Treat that as a reference, not proof of a good seal. Small details matter.
Choose an entry site and method suited to the patient, then stabilize the abdominal wall and keep the trocar aligned with the planned path. Advance with controlled pressure; avoid forcing it or making repeated, sweeping movements. Once placed, secure the cannula and connect insufflation tubing without twisting the valve. Watch the pressure and flow readings, and listen for escaping gas around the port. A falling pressure may signal a leak, but tubing, connections, and other ports can also be responsible. No seal is perfect. If readings remain unstable, pause and inspect the setup rather than simply increasing flow. Even experienced hands can rush this step. That is worth reflecting on. Follow the device instructions and local surgical protocols, and reassess the seal after repositioning or instrument exchange.
Maintaining a gas-tight trocar seal depends on more than the valve itself. During instrument use, keep the instrument aligned with the trocar opening and advance it smoothly. Angled entry or sudden movement can shift the seal and allow gas to escape. Small movements matter.
Match the instrument diameter to the trocar’s stated range, and check that the seal is seated correctly before use. Keep the valve area clear of tissue and debris, which can interfere with closure. Avoid forcing an instrument through resistance; pause and assess the setup instead. Follow the device instructions and established clinical protocols.
Instrument exchanges deserve attention. Remove tools steadily, then confirm that the valve closes before inserting another. Watch for changes in insufflation pressure and listen for a hiss, but remember that not every leak is easy to hear. Even careful handling cannot prevent every brief loss of gas. That limitation deserves honest attention. If a seal appears damaged or pressure remains unstable, stop using the affected assembly and have the clinical team assess it.
A dependable trocar seal is checked during setup and whenever pneumoperitoneum seems unstable. Monitor insufflator pressure and flow, and inspect the port, valve, and tubing connections. Listen for a faint hiss near the seal. A hiss is a clue, not proof. Pressure changes can have other causes, so check the whole gas pathway rather than blaming the trocar immediately. Follow the device instructions and local procedure. Do not increase pressure simply to mask a suspected leak.
Remove the instrument and examine the seal for tears, displacement, or trapped tissue. Clear debris only by an approved method; never probe the valve with a sharp tool. Confirm the seal matches the instrument diameter and sits evenly. Replace it if it looks stretched, cracked, or continues to leak. Check nearby connections separately, since a loose fitting can mimic a faulty seal. A seal may look sound at rest, then leak when the instrument is angled. That detail is easy to miss. After correcting the problem, reassess under normal operating conditions and communicate persistent leakage to the surgical team. Avoid forcing an instrument or adjusting components blindly.
Use the trocar and insufflation system according to their instructions for use and local protocol. Checks and corrective actions should be performed by trained operating-room personnel.
| Check area | How to check | Possible sign of leakage | Appropriate response |
|---|---|---|---|
| External tubing and connectors | Check that insufflation tubing is securely connected and free of visible damage, kinks, or loose fittings. | A loose connection, damaged tubing, or unexpected flow or pressure behavior on the insufflator. | Correct a loose connection or kink. Replace damaged components as directed by the device instructions; do not use a damaged set. |
| Trocar housing and seal assembly | Inspect the housing, seal, and access port for visible cracks, tears, displacement, or contamination. | Visible seal damage or gas escaping around the instrument entry point. | Stop using a visibly damaged trocar. Replace it with a compatible device; do not attempt an improvised repair. |
| Instrument size and compatibility | Confirm that the instrument diameter and type are permitted for the trocar seal, using the device labeling and instructions. | A poor fit, excessive play, or leakage while an instrument is in the port. | Use a compatible instrument and access port. Avoid forcing instruments through the seal. |
| Instrument insertion and movement | Observe the seal during insertion, withdrawal, and instrument movement, following the trocar instructions. | Leakage that occurs only when the instrument is moving or is partly withdrawn. | Reposition or fully seat the instrument as appropriate. If leakage persists, assess the seal and consider replacing the trocar. |
| Valve and access-port closure | Check that any valve, cap, or access-port closure is present, correctly positioned, and closed when required. | Gas escaping from an unused port or from a closure that appears loose or displaced. | Close or correctly reseat the closure according to the instructions. Replace a missing or faulty component with a compatible one. |
| Port position and tissue interface | Assess whether the port is stable and whether gas appears to escape around the access site, following the surgeon’s judgment and procedure protocol. | Leakage around the outside of the cannula rather than through its valve or seal. | The surgeon should assess port position and the access site and take appropriate procedural steps; do not manipulate the port without authorization. |
| System pressure and flow | Review insufflator readings and alarms, and compare them with the expected behavior for the setup and procedure. | Unexplained inability to maintain the set pressure, persistent high flow, or repeated alarms. | Check the full gas pathway and access sites. Follow the insufflator instructions and clinical protocol; do not rely on a single reading to locate a leak. |
| Leak confirmation and escalation | If the source is not clear, perform only checks permitted by the device instructions and local protocol, with the clinical team informed. | Leakage continues after compatible connections and closures have been checked. | Pause and escalate to the responsible clinician or biomedical support as appropriate. Replace suspect equipment rather than continuing with an unresolved leak. |
Key principle: Identify whether the leak is at an external connection, the trocar seal, the instrument interface, or the access site. Follow the device instructions and clinical protocol, and do not use equipment with suspected damage.
Match it to the procedure, instrument diameter, and expected number of exchanges. Check valve design, cannula length, and extraction needs.
Not necessarily. Seal performance can vary with the instrument, valve design, and shaft angle.
It gives 12–15 mmHg as useful context. That range does not guarantee a gas-tight seal during every exchange.
Inspect the seal for damage, confirm instrument compatibility, and follow the device instructions. Small details matter.
Angled entry or sudden movement may shift the seal and allow gas to escape. Smooth, aligned movement can help maintain closure.
Remove instruments steadily and check that the valve closes before inserting another. Even careful handling may not prevent brief gas loss.
Watch for changing insufflation pressure or listen for a hiss. Not every leak is easy to hear.
No. Testing cannot reproduce every movement, angle, or repeated exchange. I would still treat a low-leak result cautiously.
How to ensure a gas-tight seal with laparoscopic trocars? Start by selecting a trocar and seal system suited to the procedure, instruments, and access site, and inspect it for damage before use. Prepare and insert the trocar according to its instructions and established clinical technique, taking care to maintain the seal during entry. Confirm that the valve is correctly positioned and that the instrument shaft fits and moves through it without unnecessary force.
During instrument use, minimize repeated or abrupt exchanges and keep the valve clear of tissue or debris. If insufflation pressure falls or gas leakage is suspected, pause and check the trocar’s position, valve, and instrument fit. Replace or adjust a faulty component as appropriate, and reassess the seal before continuing. Careful device selection, controlled handling, and prompt leak checks help maintain a stable operative field; clinicians should follow the device instructions and their training throughout the procedure.

Centuri Medical